
AIRCHILL · Product concept
Last reviewed 18 August 2026 · Trust Center / change history
One device. Ventilation and controlled cooling.
AIRCHILL is being developed as a transport ventilator with controlled respiratory cooling for structured emergency-care workflows. The current stage is product and clinical validation: measured mechanism and preclinical safety data support the next programme, which is designed to establish patient performance and safety and then test and size clinical benefit. Regulatory approval and outcome claims follow that evidence programme.
The device
The platform as it is designed — and what of it exists.
The rendering shows the AIRCHILL platform concept: a transport ventilator with controlled respiratory cooling, patient monitoring, and a detachable handheld control unit. It is a design study. The first regulatory product is not planned as a hardware-starved or throw-away MVP. The strategy is a minimum certifiable configuration (MCC): make the hardware platform as complete as rationally possible where mature purchased or OEM modules can be integrated without disproportionate regulatory burden, while deliberately keeping the first intended purpose and claim set focused. The demonstrator further down is what physically exists today.

Design concept · rendering 2019 · not an approved product
The platform architecture is intended to be as complete as rationally possible from the first certifiable generation. AIRCHILL’s proprietary engineering novelty is concentrated in controlled respiratory cooling, the gas path, control logic and safe system integration. Most additional hardware is not intended to be developed as a new AIRCHILL subsystem. Monitoring, suction, ECG/defibrillation and telemedicine are planned primarily around established purchased components, OEM modules or standard interfaces. That makes a deliberately hardware-starved MVP less attractive: omitting mature components can save less than expected while still forcing a later integration and change-control programme. The main scope reduction therefore comes from avoiding unnecessary proprietary subsystem R&D and focusing the first intended purpose and clinical claims. Every included purchased subsystem still requires supplier qualification, interface engineering, electrical/software compatibility, risk management and system-level verification; functions that materially change classification or evidence requirements remain explicit regulatory gates.
- In the MCCTransport ventilation with controlled respiratory cooling, including the safety-critical gas path, sensing, alarms and operator control required for the intended use.
- Detachable unitHandheld control and monitoring at the patient, so the stack does not have to be reached over during a resuscitation.
- Purchased / OEM modulesSuction, patient monitoring, ECG, defibrillation and telemedicine are planned primarily through established purchased components, OEM modules or standard interfaces. They are not the core proprietary hardware development, but any integrated function still has to meet system-level interface, risk and verification requirements.
- StatusNo design freeze, no CE marking, not approved for patient use.
Rendering of the design concept, created in 2019; it illustrates the intended platform, not the current build state. No performance, safety or outcome claim is derived from it. Technology readiness of the physical demonstrator is conservatively rated at TRL ≈ 4.
Mechanism
Four controlled steps between the gas source and the patient.
The V1 media architecture is now defined: liquid oxygen is the sole media source. It is vaporized for ventilation and thermally conditioned through a gas-tight ambient heat exchanger to the target inspiratory temperature. The remaining engineering problem is control: temperature, flow, FiO₂, humidity, pressure, oxygen compatibility and airway integrity must all hold at once.

The demonstrator used in the preclinical experiments. Technology readiness is conservatively rated at TRL ≈ 4. The V1 media architecture is defined as a liquid-oxygen single-media path; detailed mechanical, control and manufacturable product implementation remains under development.
Own photograph. TRL classified per the EU definition, Horizon Europe Annex G.

Infrared thermography at the start of cold air delivery and 23 minutes in. Surface temperature drops visibly; quantification gave roughly 0.3 °C per minute under endonasal delivery.
Final report, BMBF grant 031A530, University Medical Center Hamburg-Eppendorf, 2017.
The gas path
Temperature is the axis, not a label.
The same four steps, drawn as what they are: a controlled temperature profile from a cryogenic source to the patient. The rise inside the airway at the right of the chart is the heat that leaves the patient.
Swipe the chart sideways to follow the gas path →
Airway safety
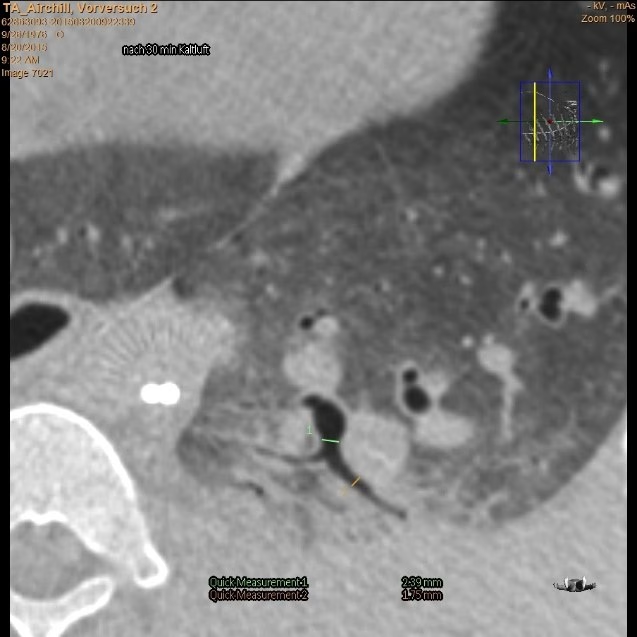
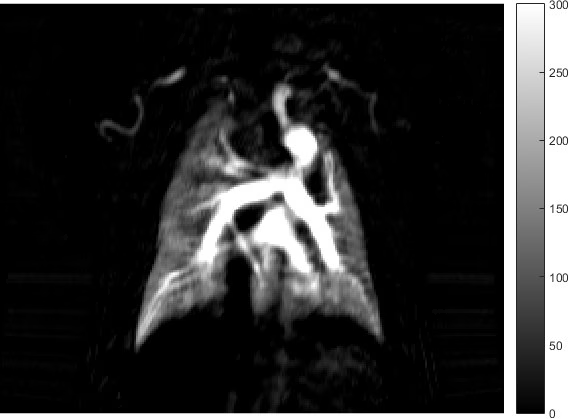
What six hours of cold gas did to the lung.
Nothing measurable. That is the finding, and it is the one a notified body asks for first.
The circuit
The breathing circuit, drawn as a system.
A schematic rather than an anatomical section — this is the drawing a developer and a notified body actually read, and it is where the open-loop decision becomes visible.
Swipe the schematic sideways →
First certifiable configuration
A broad hardware platform with a deliberately focused first claim set.
The first approval programme is designed around hardware completeness where integration relies on mature purchased or OEM technology, while regulatory ambition stays focused. The minimum certifiable configuration (MCC) keeps proprietary development concentrated on ventilation, controlled cooling and safe system integration. Additional mature hardware can be designed into—and, where classification and verification burden remain proportionate, included in—the first certifiable platform. The primary scope lever is the first intended purpose and claim set, not an artificially incomplete hardware build.
Minimum certifiable configuration (MCC)
Transport ventilation with controlled respiratory cooling · complete safety-critical gas path · temperature, flow, FiO₂, humidity and pressure control · sensors, alarms, operator controls, cleaning and service concept · the verification package needed for the intended use.
Platform functions beyond the proprietary core
Monitoring, suction, ECG/defibrillation and telemedicine are expected primarily to use established purchased components, OEM modules or standard interfaces. That can avoid duplicating mature subsystem R&D; the remaining work is supplier qualification, interface definition, risk management and verification of the integrated AIRCHILL system.
Clinical workflow
Designed for gated adoption, not for a shortcut.
Any clinical workflow needs inclusion criteria, airway-management rules, monitoring, stop criteria and training. Those belong in protocol, usability and risk-management work before routine use.
Eligibility and setup
Protocol-defined selection, device checks, trained operators.
Ventilation and monitoring
Controlled intervention with respiratory, temperature and safety monitoring.
Handover and follow-up
Documented transition into the receiving hospital’s temperature-control pathway.
Differentiation
How AIRCHILL’s engineering path differs from earlier selective-cooling systems.
Integration, safety data, timing
Cooling that runs on the ventilation already in place rather than as a second device. Preclinical airway safety for the endotracheal route is documented over six hours at −20 °C. RhinoChill works with perfluorohexane; our route does not.
Make lower-airway cooling measurably stronger and more uniform
The 2017 setup showed low, locally limited endotracheal cooling because of dead-space ventilation while the endonasal route produced a stronger local effect. That result defines a concrete optimisation target: flow, inspiratory temperature, circuit geometry, humidity/condensation and treatment timing. The next programme is designed to quantify whether a redesigned lower-airway system can create a larger, reproducible target-organ thermal effect while preserving ventilation and airway safety.
RhinoChill has carried a CE mark for commercial use, class IIb, since April 2011 (NICE MIB4). PRINCESS (Nordberg P et al., JAMA 2019;321:1677–1685, n = 677) missed its primary endpoint of good neurological outcome at 90 days. No CE-marked device was found that cools through the lower airway in combination with ventilation; the absence of a find is not proof, and EUDAMED and freedom-to-operate searches are outstanding.
Granted intellectual property
One patent family, granted in Europe and the United States.
The core idea — a transportable device that lowers body temperature through the airway with a cooled, oxygen-carrying gas flow — is protected by granted rights in Europe and the United States from a September 2016 priority. The public patent records are linked below. Inventor Fabian Temme is the sole patent holder; the university is not a co-owner of the patents.
Transportable device and system for lowering the body temperature of a mammal over the airways, in particular of a human, by means of a cooled, oxygen-containing gas flow
Transportable device, system and method for providing a cooled, oxygen-containing gas flow
The granted rights are held solely by inventor Fabian Temme. The university is not part of the patent ownership structure, so there is no institutional co-owner. This creates a concentrated chain of title and a direct path for any future corporate assignment or exclusive licence to the operating company.
Checked against the public patent registers on 8 August 2026. Inventor and sole patent holder: Fabian Temme. The university is not a co-owner of the granted patent rights; the ownership structure is concentrated with the founder. Records: EP3509683B1 · US11395900B2 · WO2018046128A1. Term runs to 9 September 2037 subject to fees and legal validity. Validation states, annuity payments, opposition status and the scope of the granted claims against the planned product have not been assessed.
Validation pathway
From development platform to clinical validation.
The next programme is designed to progress AIRCHILL from TRL ≈ 4 through product verification, first-in-patient performance and safety, and indication-specific efficacy studies. CE marking, FDA clearance and clinical claims remain development milestones until the required evidence and regulatory review are complete.
Ventilation, thermal systems, verification.
If you build emergency ventilators, thermal systems or airway consumables, we would like to talk.